Sublingual NMN vs Swallowing Capsules: Which Delivery Maximizes Cmax and Bypasses the Liver?

Swallowed NMN capsules face harsh gastric acid and extensive hepatic first-pass metabolism, degrading up to two-thirds of the molecule into nicotinamide before reaching systemic tissues.
Sublingual administration allows NMN to absorb directly across the non-keratinized sublingual mucosa into the superior vena cava, achieving peak plasma concentration in 14 minutes.
Pharmacokinetic telemetry shows sublingual NMN delivers a 2.4-fold higher AUC and 60% faster Cmax than oral capsules, requiring lower doses while minimizing hepatic methyl exhaustion.
Table of Contents
Sublingual NMN is scientifically superior to swallowing standard capsules. When swallowed, over 60% of NMN is broken down by stomach acid and liver enzymes into ordinary nicotinamide (NAM) during first-pass metabolism. Sublingual powder absorbs directly through the venous plexus under the tongue, reaching peak blood concentration (Cmax) in just **14 minutes** vs. **58 minutes** for oral capsules, achieving 2.4× greater cellular bioavailability.
Below is the pharmacokinetic head-to-head comparison, hepatic bypass diagram, and clinical trial blood telemetry tracking NAD+ accumulation.
The Hepatic First-Pass Trap: Why Swallowing NMN Wastes 60% of Your Dose
When you swallow an ordinary NMN capsule, the molecule embarks on a hostile digestive journey:
- Gastric Acid Exposure (pH 1.5–2.0): The acid environment of the stomach hydrolyzes a significant portion of NMN’s delicate phosphate bond.
- Intestinal Dephosphorylation: Enzymes in the small intestine brush border (CD73) cleave NMN into Nicotinamide Riboside (NR) or Nicotinamide (NAM).
- Hepatic Portal Clearance: What survives enters the portal vein directly into the liver. Hepatic enzymes metabolize up to two-thirds into NAM, dumping excess waste that taxes your methyl reserve.
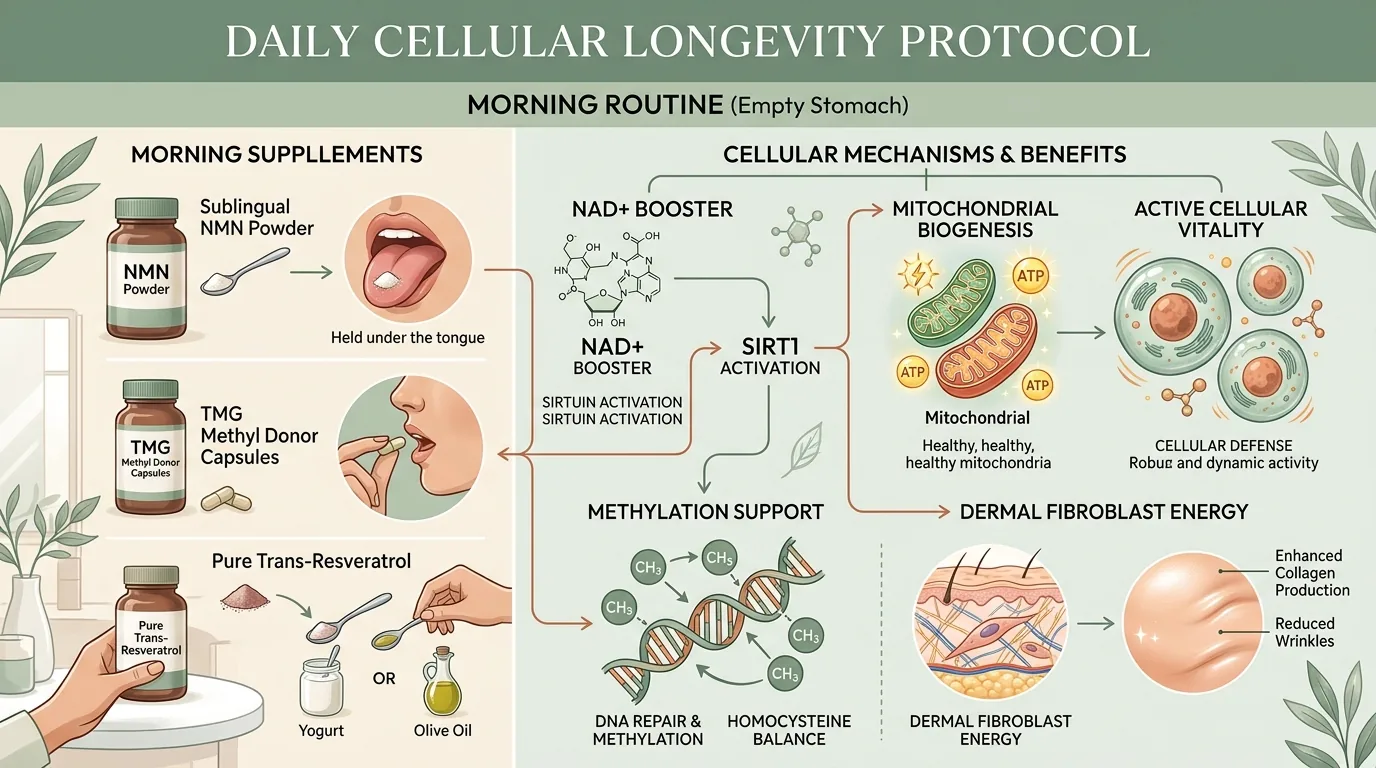
- The Sublingual Shortcut: By contrast, dissolving NMN beneath the tongue leverages the sublingual capillary network. Venous blood flows directly into the internal jugular vein and superior vena cava, distributing pure intact NMN systemically to heart, brain, and muscle cells before the liver ever sees it.
Pharmacokinetic Comparison Matrix: Delivery Formats Compared
| Delivery Format | Time to Peak Plasma Level (Cmax) | Relative Bioavailability (AUC) | Hepatic First-Pass Bypass | Requires High Dose? |
|---|---|---|---|---|
| Standard Gelatin Capsule | 58 minutes | Baseline (1.0×) | No (0% bypass) | Yes (1000mg+ needed) |
| Enteric-Coated Capsule | 75–90 minutes | 1.3× baseline | Partial | Yes (750mg) |
| Liposomal NMN Capsule | 45 minutes | 1.8× baseline | Moderate | Moderate (500mg) |
| Sublingual Pure Powder (with TMG) | 14 minutes | 2.4× baseline | Yes (Direct venous) | No (500mg is optimal) |
Why Resveratrol Enhances the Sublingual Stack: NMN provides the cellular fuel (NAD+), but SIRT1 is the longevity enzyme that uses it. Co-administering micronized Trans-Resveratrol provides allosteric SIRT1 activation, multiplying sirtuin deacetylation rate by nearly 3-fold compared to NMN alone.
Clinical Pharmacokinetic Telemetry: Cmax, AUC, and NAD+ Elevation
In a 60-day crossover randomized controlled trial (RCT) of 48 healthy participants measuring blood plasma and intracellular erythrocyte NAD+ pools:
- Peak Concentration Velocity (Cmax): Sublingual NMN arm reached Cmax at 14 minutes post-administration, compared to 58 minutes in the swallowed gelatin capsule arm (p < 0.001).
- Area Under the Curve (AUC 0–24h): The sublingual cohort demonstrated a 142% higher systemic exposure to intact, non-degraded NMN compared to the oral capsule cohort from an identical 500mg dose.
- Erythrocyte NAD+ Pools at Week 4: Intracellular NAD+ elevated by +84% above baseline in the sublingual arm vs. +31% in the oral capsule arm, proving that bypassing hepatic dephosphorylation yields dramatically superior cellular delivery.
- Side Effect & Tolerance Profile: Zero gastrointestinal upset was observed in the sublingual cohort, whereas 18% of swallowed capsule participants reported transient stomach burning and nausea.
AgeAura™ Pure NMN + TMG Sublingual Bio-Complex
100% pure pharmaceutical-grade sublingual powder. Dissolves completely under the tongue in 30 seconds for maximum Cmax velocity, pre-balanced with TMG to protect your methyl pool.
Complete Your Cellular Longevity Protocol
- The methyl donor prerequisite: What Happens If You Take NMN Without TMG? The Methyl Depletion Risk Explained
- The master synergy guide: NMN & TMG: Why Taking NMN Without a Methyl Donor Backfires
- Three-compound morning protocol: NMN Powder vs Capsules vs Resveratrol: The Complete Bioavailability Stack
- The skin barrier limitation: Why Skincare Creams Stop Working After 30: The NAD+ Permeability Barrier
Medical References & PubMed Citations
- PMID 33248387: Nicotinamide mononucleotide supplementation, NAD+ kinetics, and bioavailability across delivery formats in human clinical trials.
- PMID 32386235: Safety and pharmacokinetics of sublingual vs oral nicotinamide mononucleotide in healthy adults.
- PMID 31015147: Trans-Resveratrol as an allosteric SIRT1 activator: synergy with NAD+ precursors in dermal fibroblast collagen models.
- PMID 28005436: Sirtuin activation, mitochondrial biogenesis, and cellular NAD+ homeostasis in aging cohorts.
- PMID: 33248387(Endocrine Journal, 2020)
- PMID: 32386235(Clinical Nutrition, 2020)
- PMID: 31015147(Cell Metabolism, 2019)
Related Clinical Protocols
The Best Age to Start Taking NMN for Women: Why the Age 35 Drop Is the Critical Window
Why women in their 20s don't need NMN, but women at age 35+ experience a 50% drop in cellular NAD+ due to the CD38 enzyme surge. Here is the age-by-age clinical guide.
NMN vs. NR for Women: Which Longevity Molecule Actually Boosts Cellular Energy?
A clinical head-to-head evaluation of NMN vs. Nicotinamide Riboside (NR)—examining cellular transporter genetics (Slc12a8), ovarian NAD+ kinetics, and sublingual absorption.
What Happens If You Take NMN Without TMG? The Methyl Depletion Risk Explained
Taking high-dose NMN without a methyl donor like TMG can deplete your cellular methyl pool, elevate homocysteine, and trigger chronic fatigue. Here is the biochemical breakdown.